I have masked the company and product names to follow NDA and privacy rules.
UX Design Internship · 2026
Surgical Console
- The problem
- A surgery team had one second to understand a screen. Scrub nurses could not see what the surgeon pointed at.
- My part
- I designed three fixes for a surgical console: arm identity, a gallery with a video editor, and live annotation.
Before
After
The story in short
A surgery team had one second to understand a screen. Nurses could not tell which robotic arm needed help. Residents could not review video. Scrub nurses could not see what the surgeon pointed at. I designed three fixes for a surgical console: arm identity, a gallery with a video editor, and live annotation. Engineering had limited time, so I did not plan one huge redesign. I chose three steps: crawl, walk, run.
My contribution
What I did
- Designed all three projects
- Restructured 30+ screens and refined 100+ components
- Wrote the component rules
- Mapped voice-assisted workflows
- Ran my own heuristic review: 6 of 10 fixed
- Built the Figma prototype
The team and others
- Guided by a design mentor and a clinical supervisor (names masked)
- Methods
- Heuristic review, exploratory usability testing, A/B tests, V1 to V6, prototype
My backgroundM.S. Information Science (HCI), UNC Chapel HillB.S. Computer Science
The setup
The problems
Project 1 · Arm identity
Which arm is it?
- The arm was only a number.
- A nurse had to match it to a real arm in the room.
Success: the right person knows which arm, and what to do.
Project 2 · Gallery and video editor
Where is that moment?
- The old editor worked on still images only.
- A resident had to scrub through an hour of footage.
Success: find one moment without scrubbing.
Project 3 · Live annotation
What is the surgeon pointing at?
- Scrub nurses at the wall monitor could not see it.
- The surgeon’s hands stayed on the controls.
Success: a mark reaches the main screen within a second.
The goal
Shared awareness at a glance: everyone in the room knows which arm needs attention and what the surgeon is looking at.
The old screens showed real patient video, so I redrew them as wireframes. Project 3 had no old screen: the old design had no way to mark the live video.
Three projects
Arm identity
A color bar shows which arm has an error or warning.
Gallery and video editor
A gallery named by procedure step, and a video editor.
Live annotation
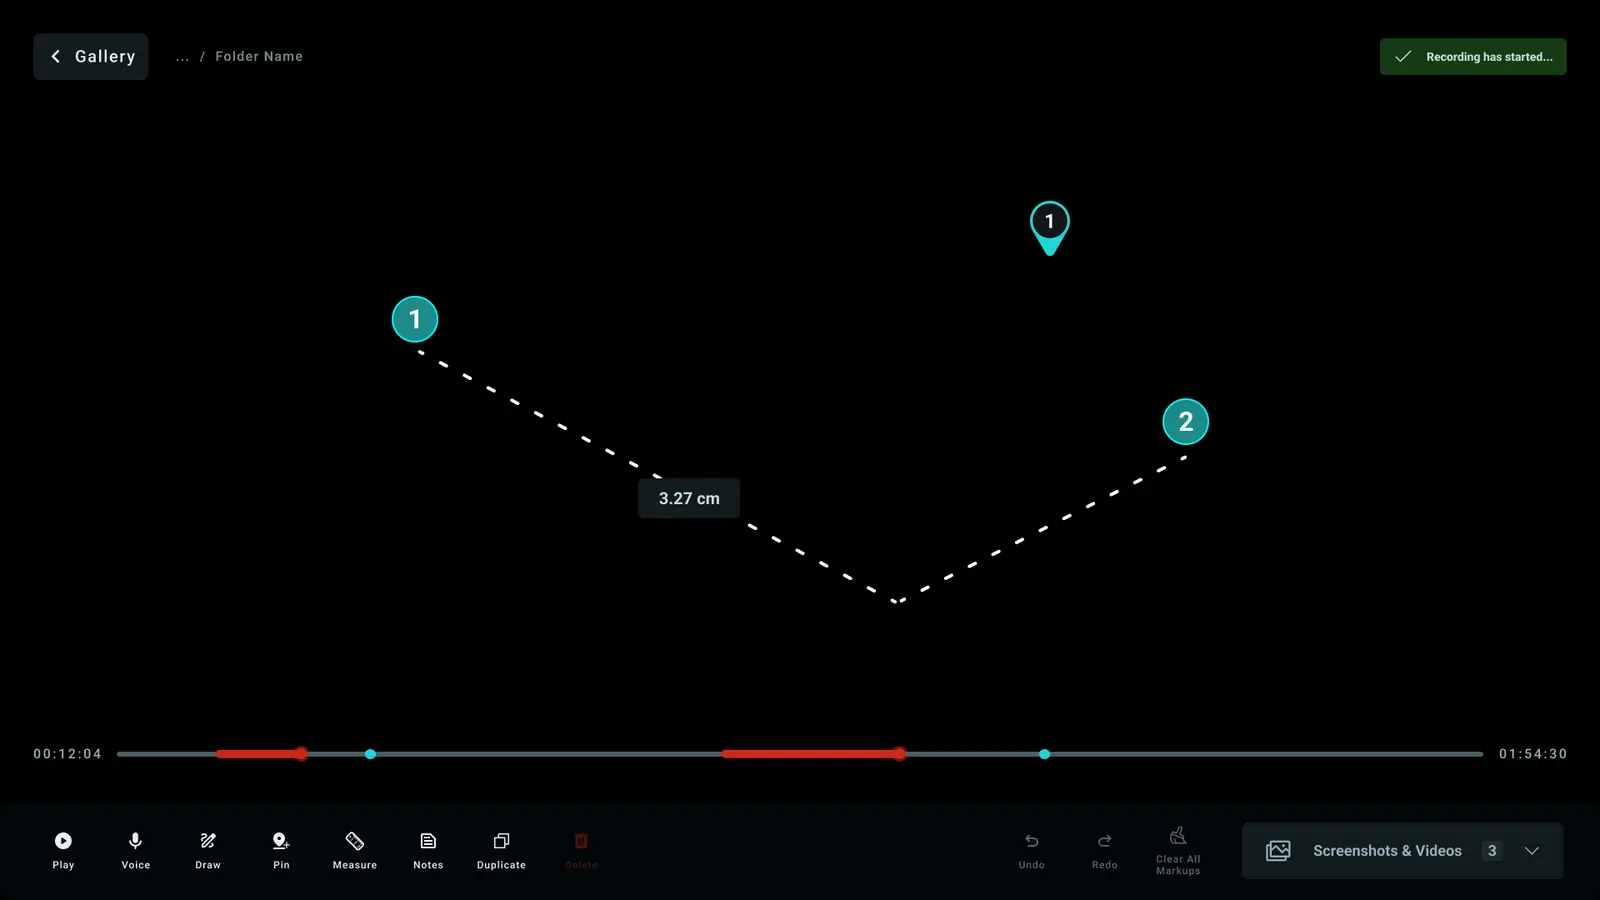
Marks made on a tablet appear on the main screen.
Constraints
Tight timelines
In development for 8 years, so requirements had to move quickly.
Many stakeholders to align
Surgeons, engineers, PMs and executive leadership.
The operating room
Screen distance, lighting, gloves and noise.
The core constraint
Surgeons glanced at it for one second, so every action had to feel instant.
The product
Users and environment
At the console. Eyes in the 3D viewer, hands on the controls.
Sterile, by the patient. Watches the wall monitor from 6 feet.
Walks the room. Answers alerts and runs recording.
At the machine, before or after surgery. Finds hardware faults.
Environment constraints
Bright endoscope feed
Warm interface colors looked like anatomy.
Brief, fragmented attention
Surgeons looked for only a second at a time.
Safety alerts first
Machine safety warnings beat every other message.
Engineering & stakeholder trade-offs
Annotation became a mode
Early hypothesis
If surgeons could mark, measure and save images on the live video without looking away, everyone in the room would see what the surgeon saw.
Annotation took 6 versions (pills, switches, toggles). I ended with a mode and a check button to exit.
- V1
Watch and Annotate segments
Watching is not a mode.
- V2
A switch in the toolbar
It looked like one more tool.
- V3
A floating glass pill
Too prominent over the video.
- V4
Tap the pill again to leave
Leaving needs its own button.
- V5
Done with a cross icon
A cross means cancel; Done means keep.
- V6
A named mode, ended by a round tick
The current version.
What I learned
It was a state problem, not a styling one. Once I designed the mode, the button was easy.
Strategy
Engineering had limited time, so I did not plan one huge redesign. I chose three steps:
- Crawl
Fit into the old layouts
I added basic capture, pin, and measure tools to the old editor.
- Walk
Rebuild with components
I made annotation its own mode and used the new console grid.
- Run
Use the same rules everywhere
I used one alert scale and one component library in the editor, gallery, and service screens.
Vision & principles
The team’s main goal was “designing for confidence.” Six principles came from it.
Informed control
You can tell what the system did and will do.
Trust and reliability
The same tap gives the same result.
Situational awareness
The anatomy matters most.
Extensibility
Components first, so one color scale works everywhere.
Clarity
Every mode is named and has a way out.
Familiarity
Controls people already know.
Lo-fi sketches
Component system
I wrote the component rules first, so every screen looks and acts the same.



Rule 1 · Severity
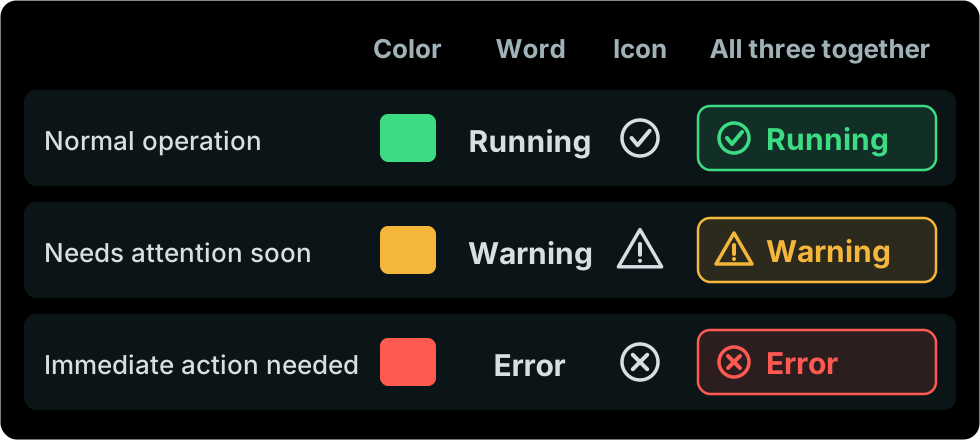
One alert scale
Green running, amber warning, red error, grey inactive. Cyan only for selection.
Rule 2 · Identity
Arms keep their own color
Shown only as a thin bar on top of the panel.
Tools versus actions
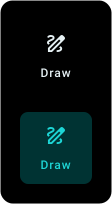
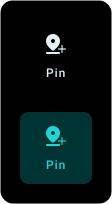
An active tool is a solid block; actions stay outlines. Only Delete is red.
Saying it three ways
Color, word and icon together, for color-blind staff.
Project 1 · Arm identity
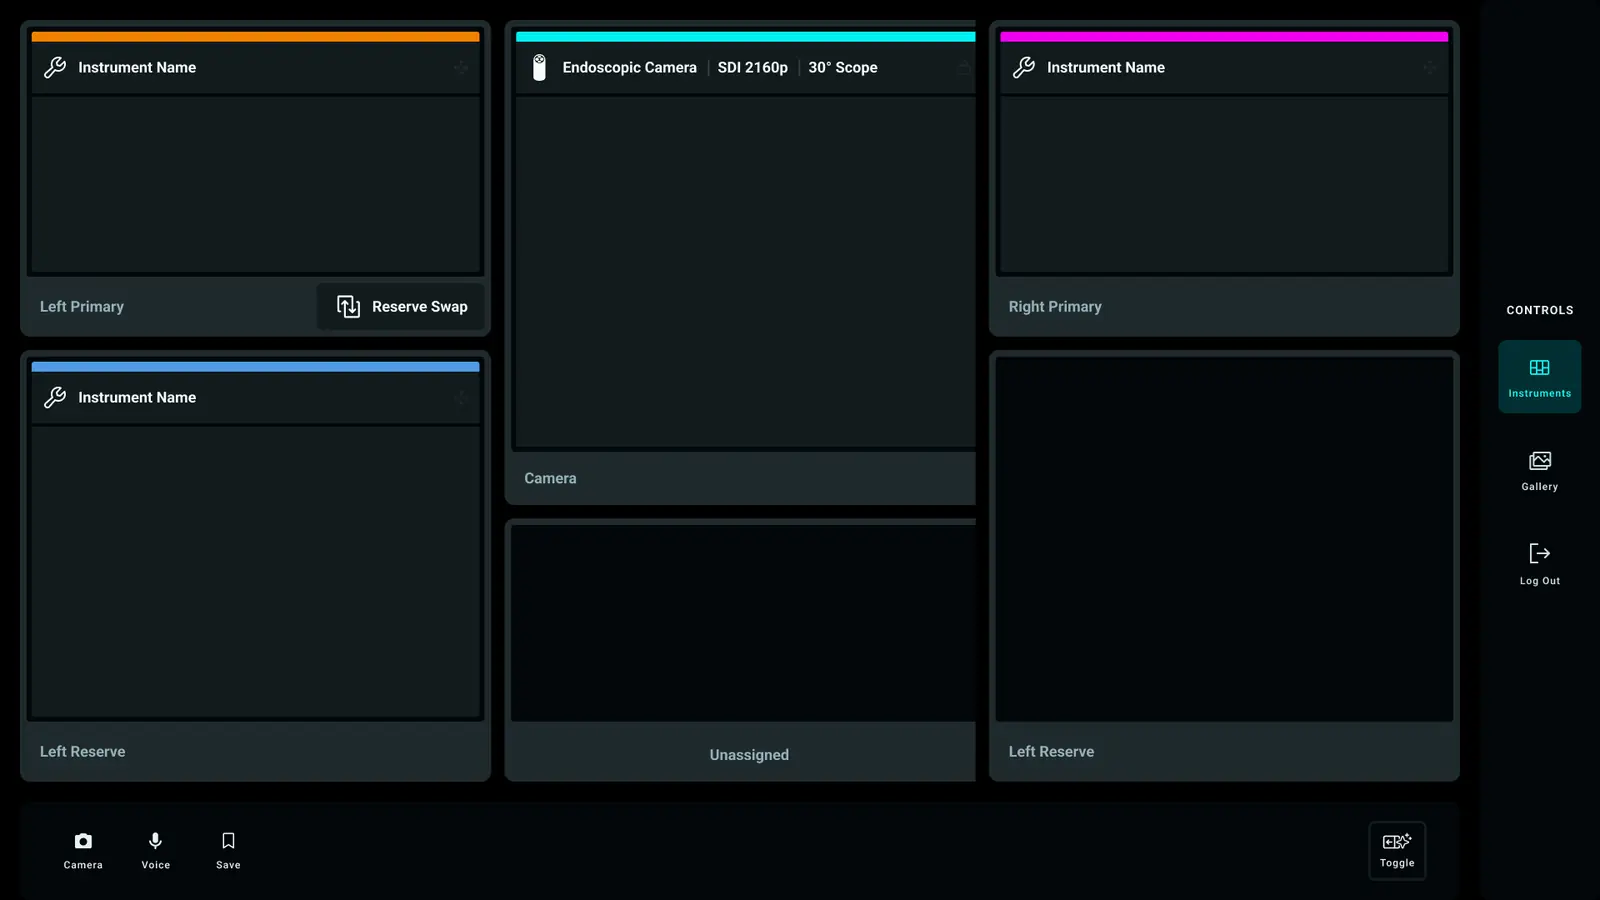
I kept each arm’s own color, shown only as a bar along the top of the panel.
The state shows as a dot and a word: Running, Warning, Error or Inactive.
Instead of
Filling the panel with the arm color. It hid which arm it was and what it was doing.
Arm sandbox
Interactive
Find the arm that needs help
Every arm, its own color, one second. Switch between the designs I tested, from the old number-only panels to the final design, and set each arm’s state. Then take the glance test: the screen shows for one second, and you pick the arm that needs help.
- Arm 1Running
- Arm 2Warning
- Arm 3Error
- Arm 4Inactive
Which arm needs help?
Arm 1
Arm 2
Arm 3
Arm 4
Press Glance test · 1s above. The console shows for one second, then you pick the arm that needs help. Try it with each design.
Project 2 · Gallery and video editor
The editor handled video
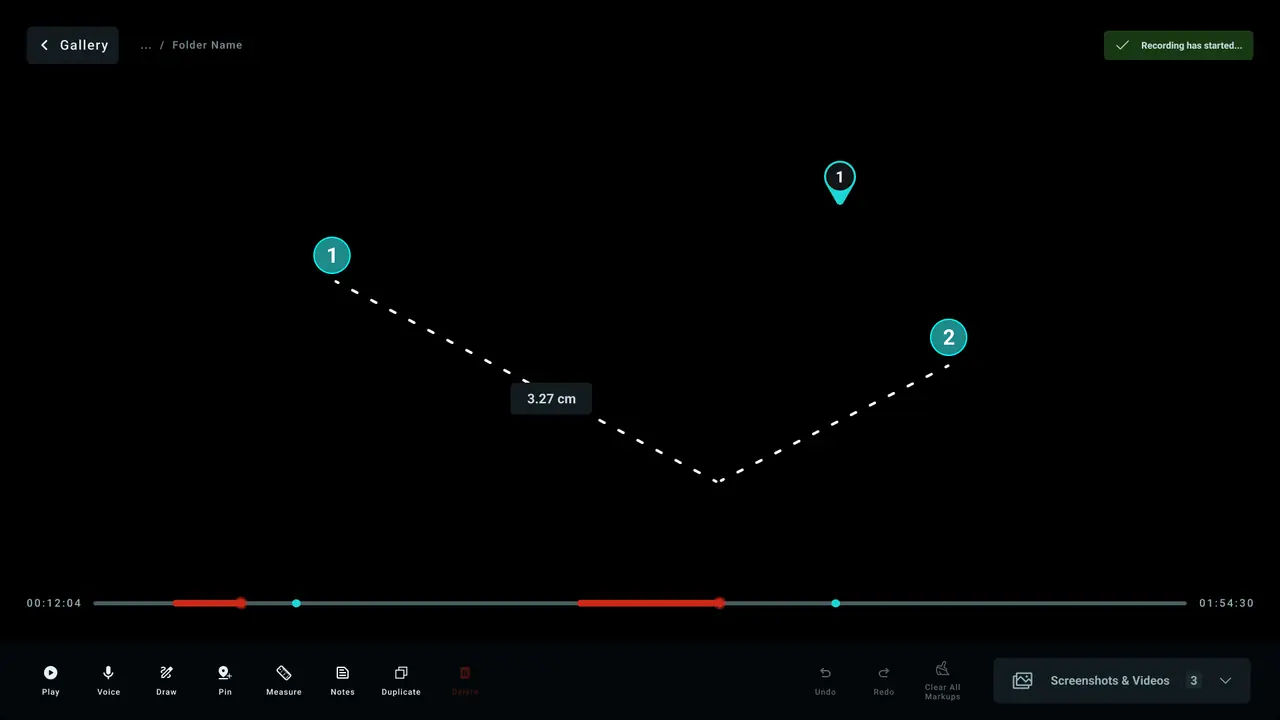
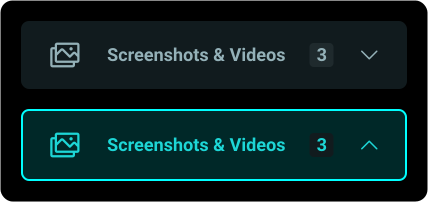
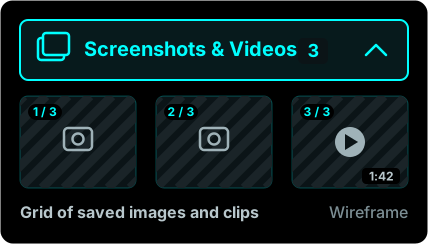
A timeline marks recordings and pins.
Instead of: still images only.
One labeled tool bar
Every tool in one bottom bar, each with a word.
Instead of: a side panel of icon tabs.
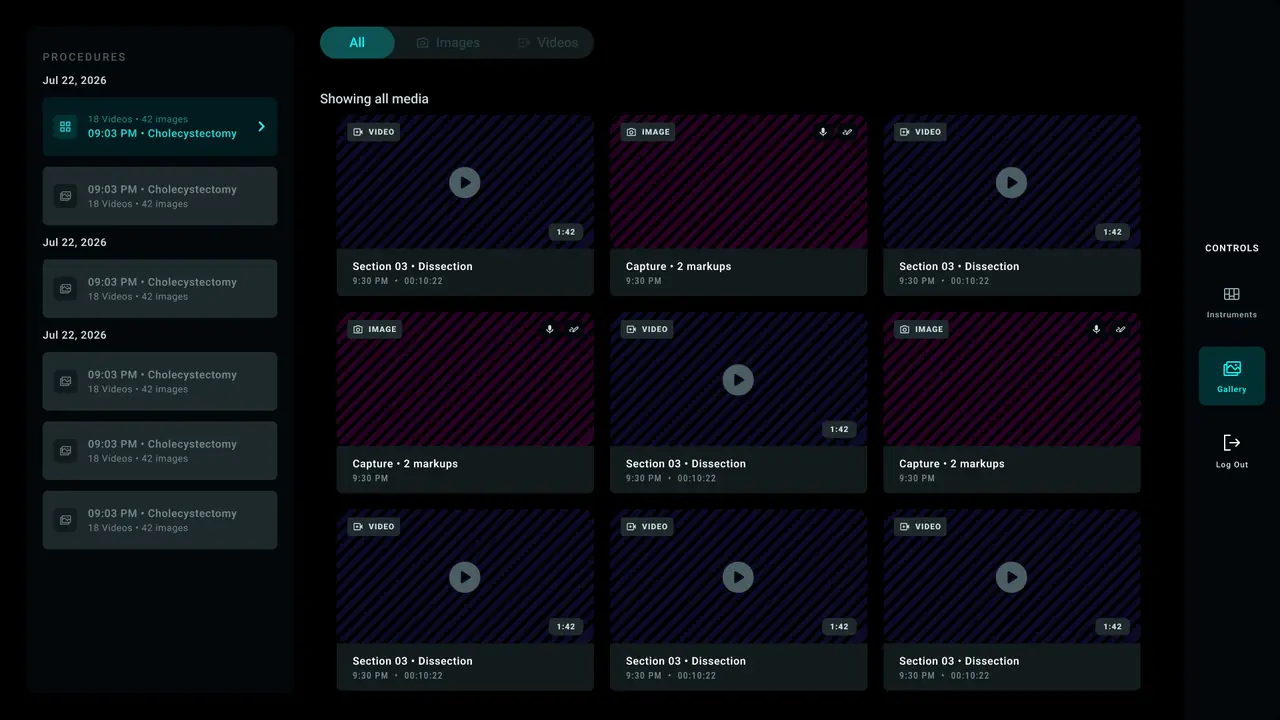
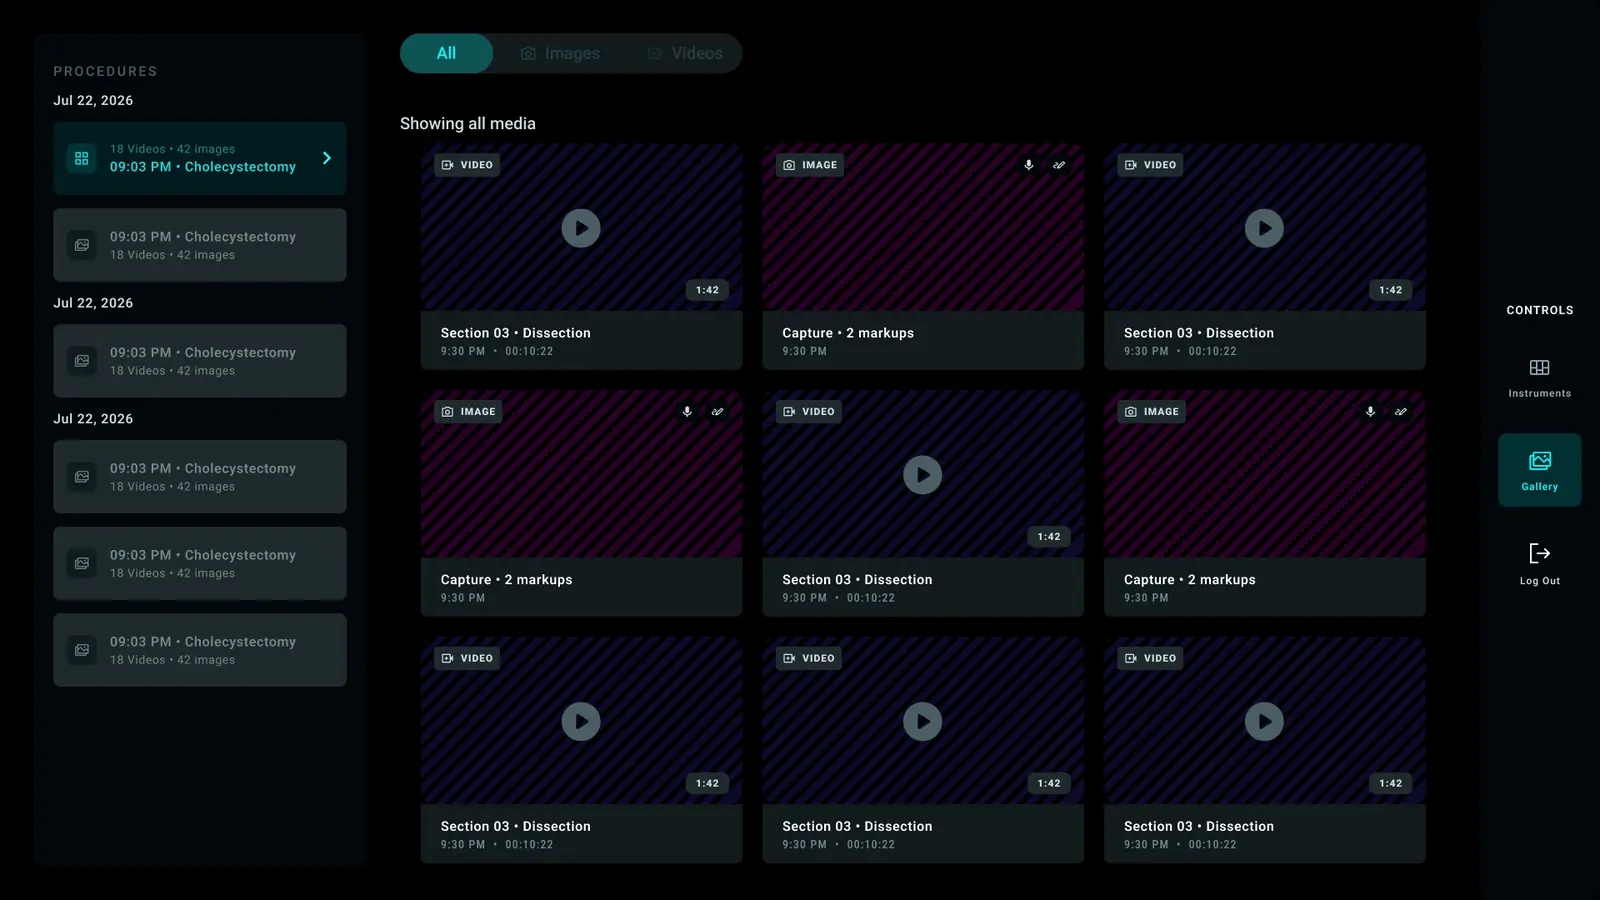
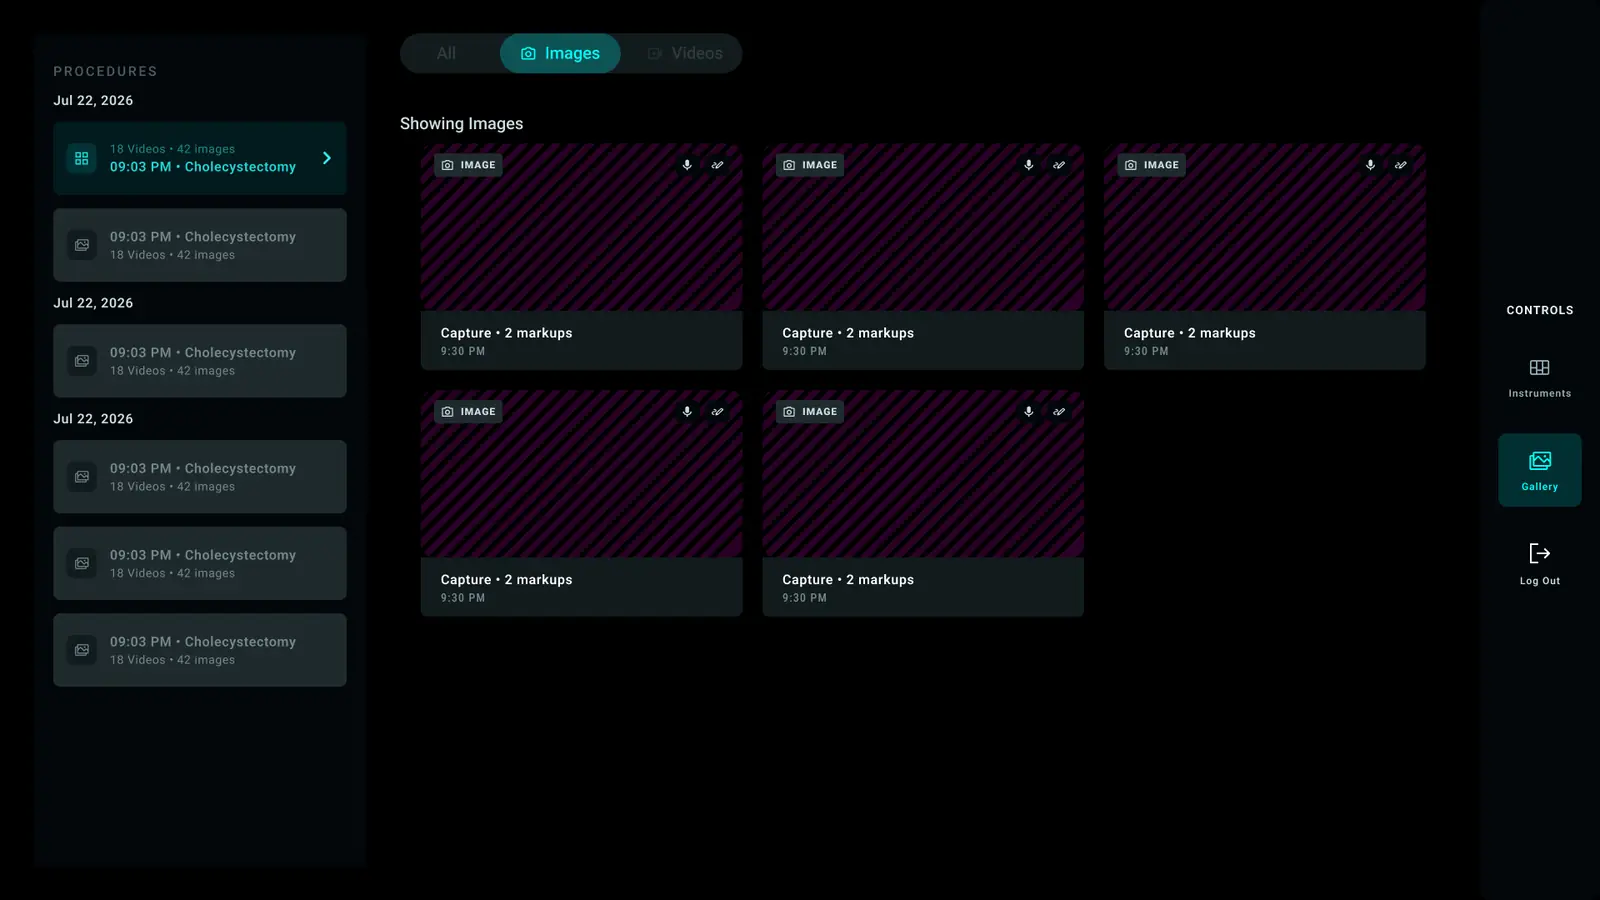
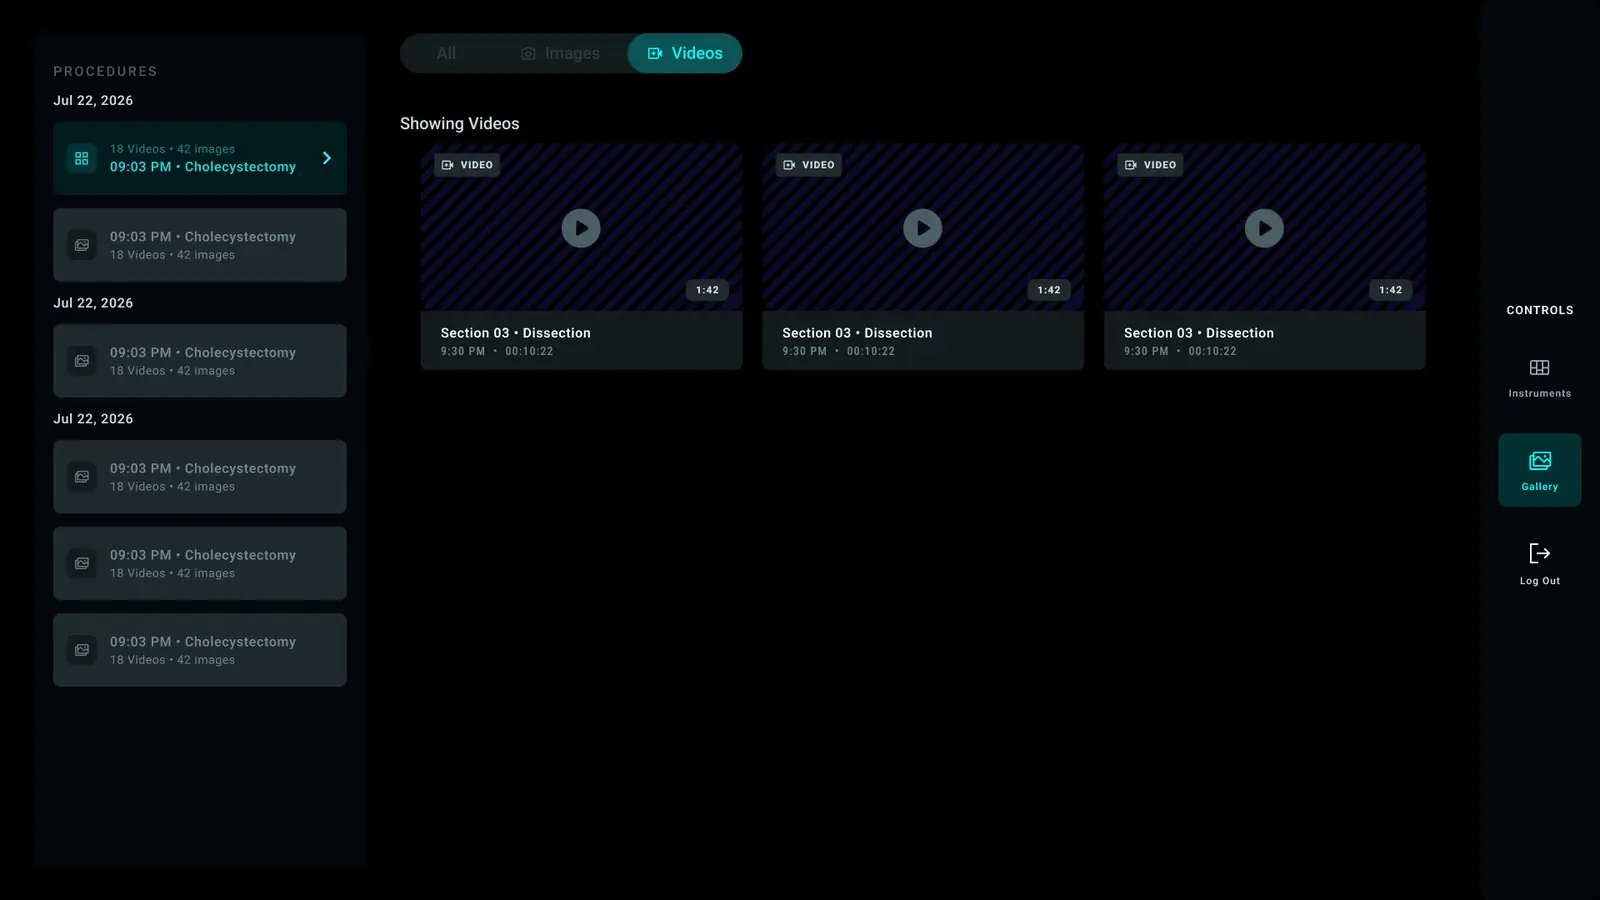
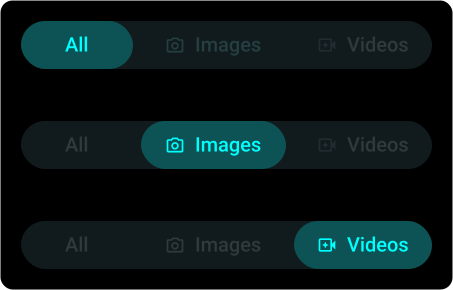
One gallery filter
All, Images and Videos share one track.
Instead of: separate filter chips.
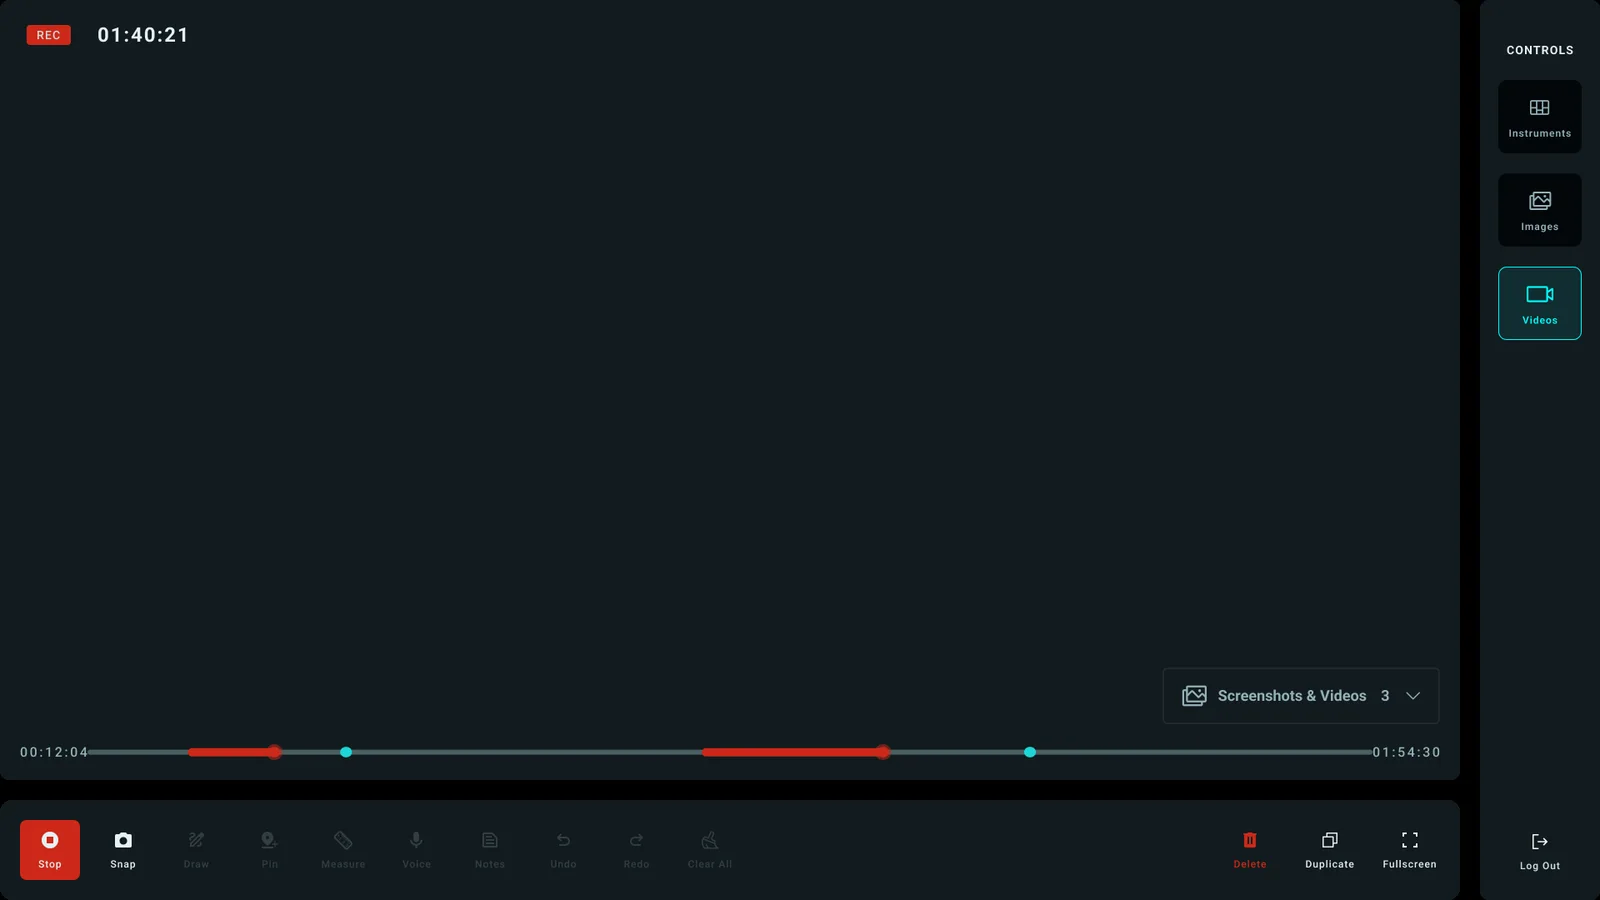
Recording changed the screen
A red Stop, and the markup tools dim.
Instead of: a state that looked like any other.
Inside the video editor
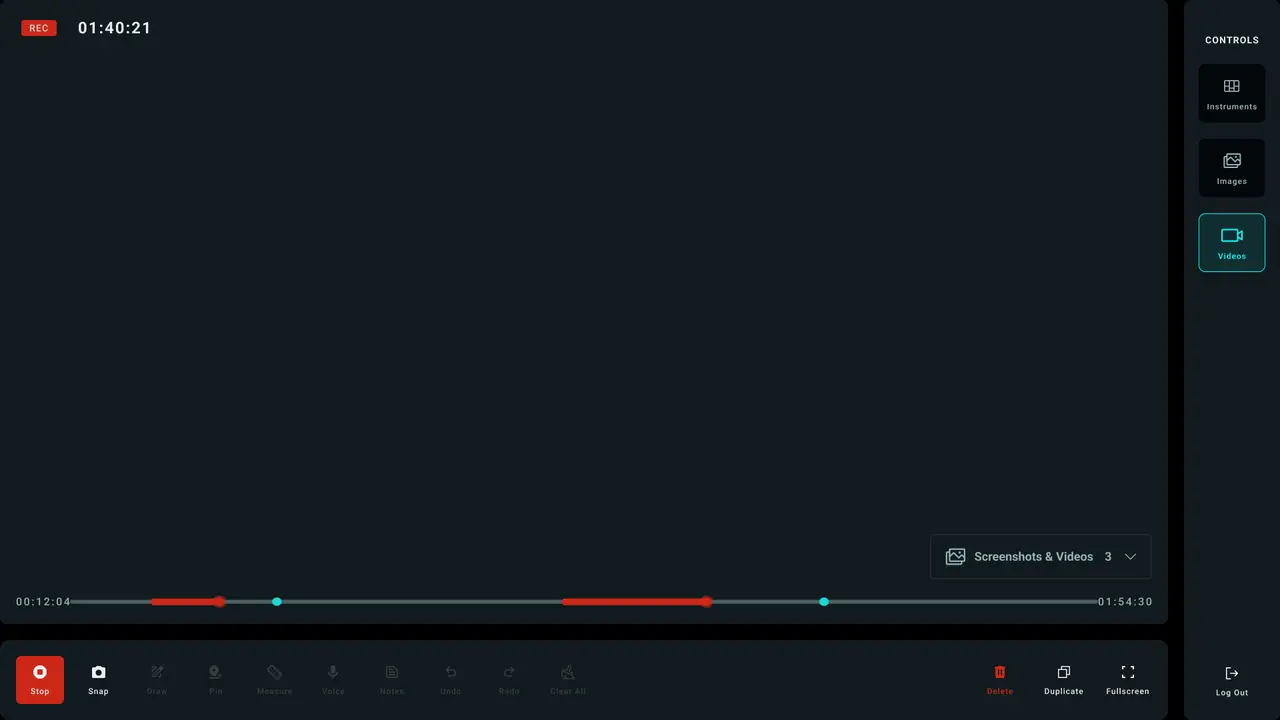
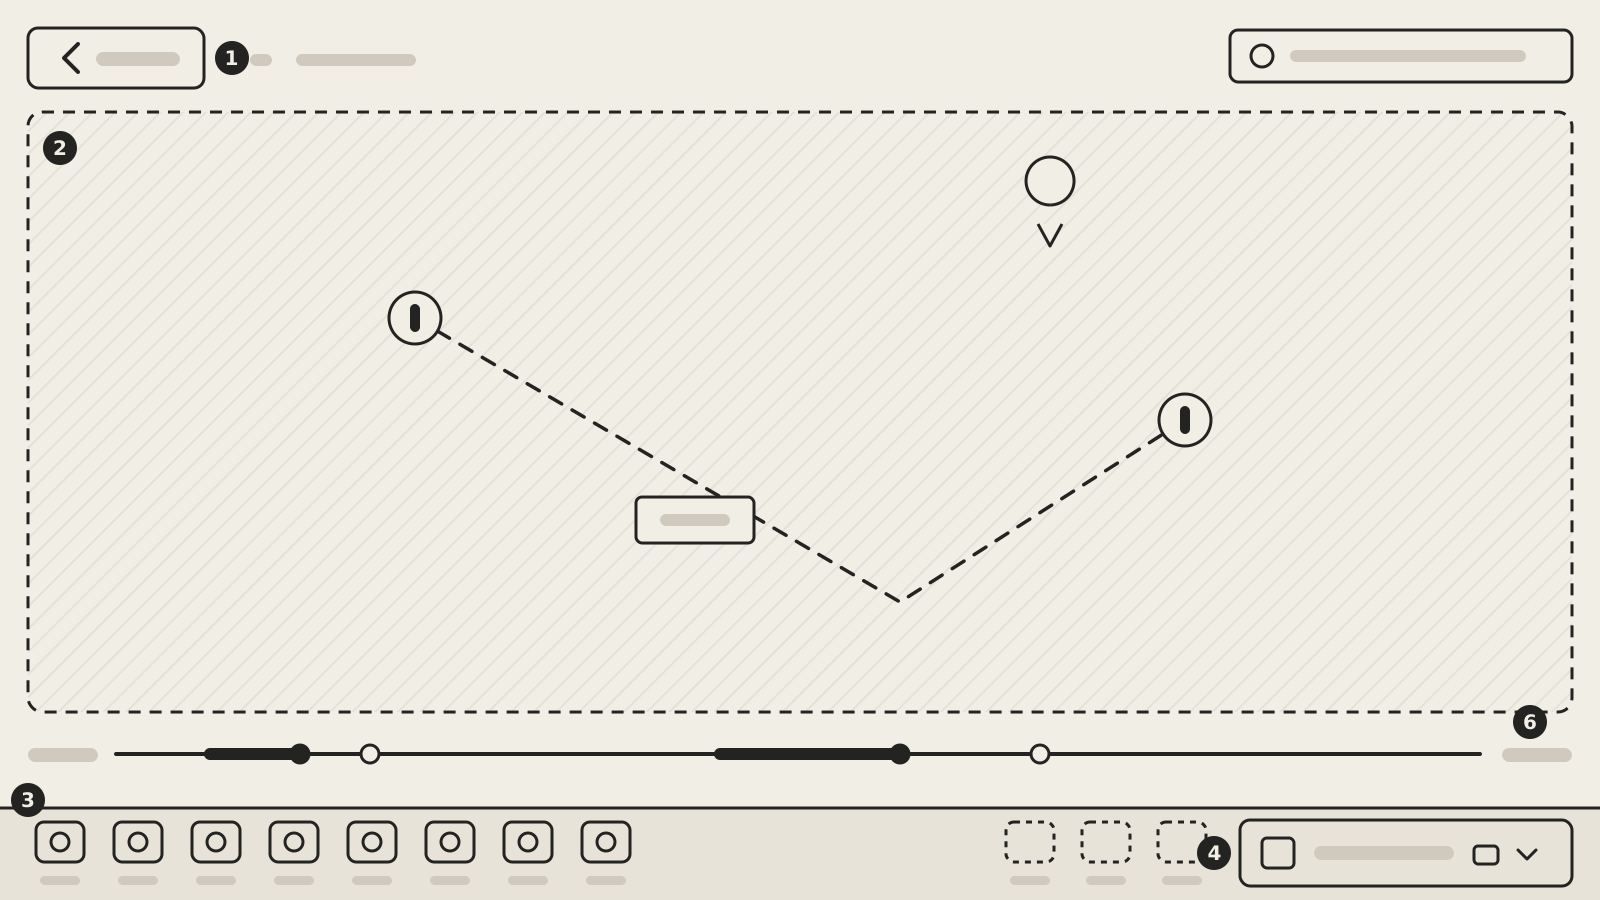
I placed each region by how often people look at it and reach for it: the live video, marks and action ribbon all the time; status and timeline sometimes; menus rarely.
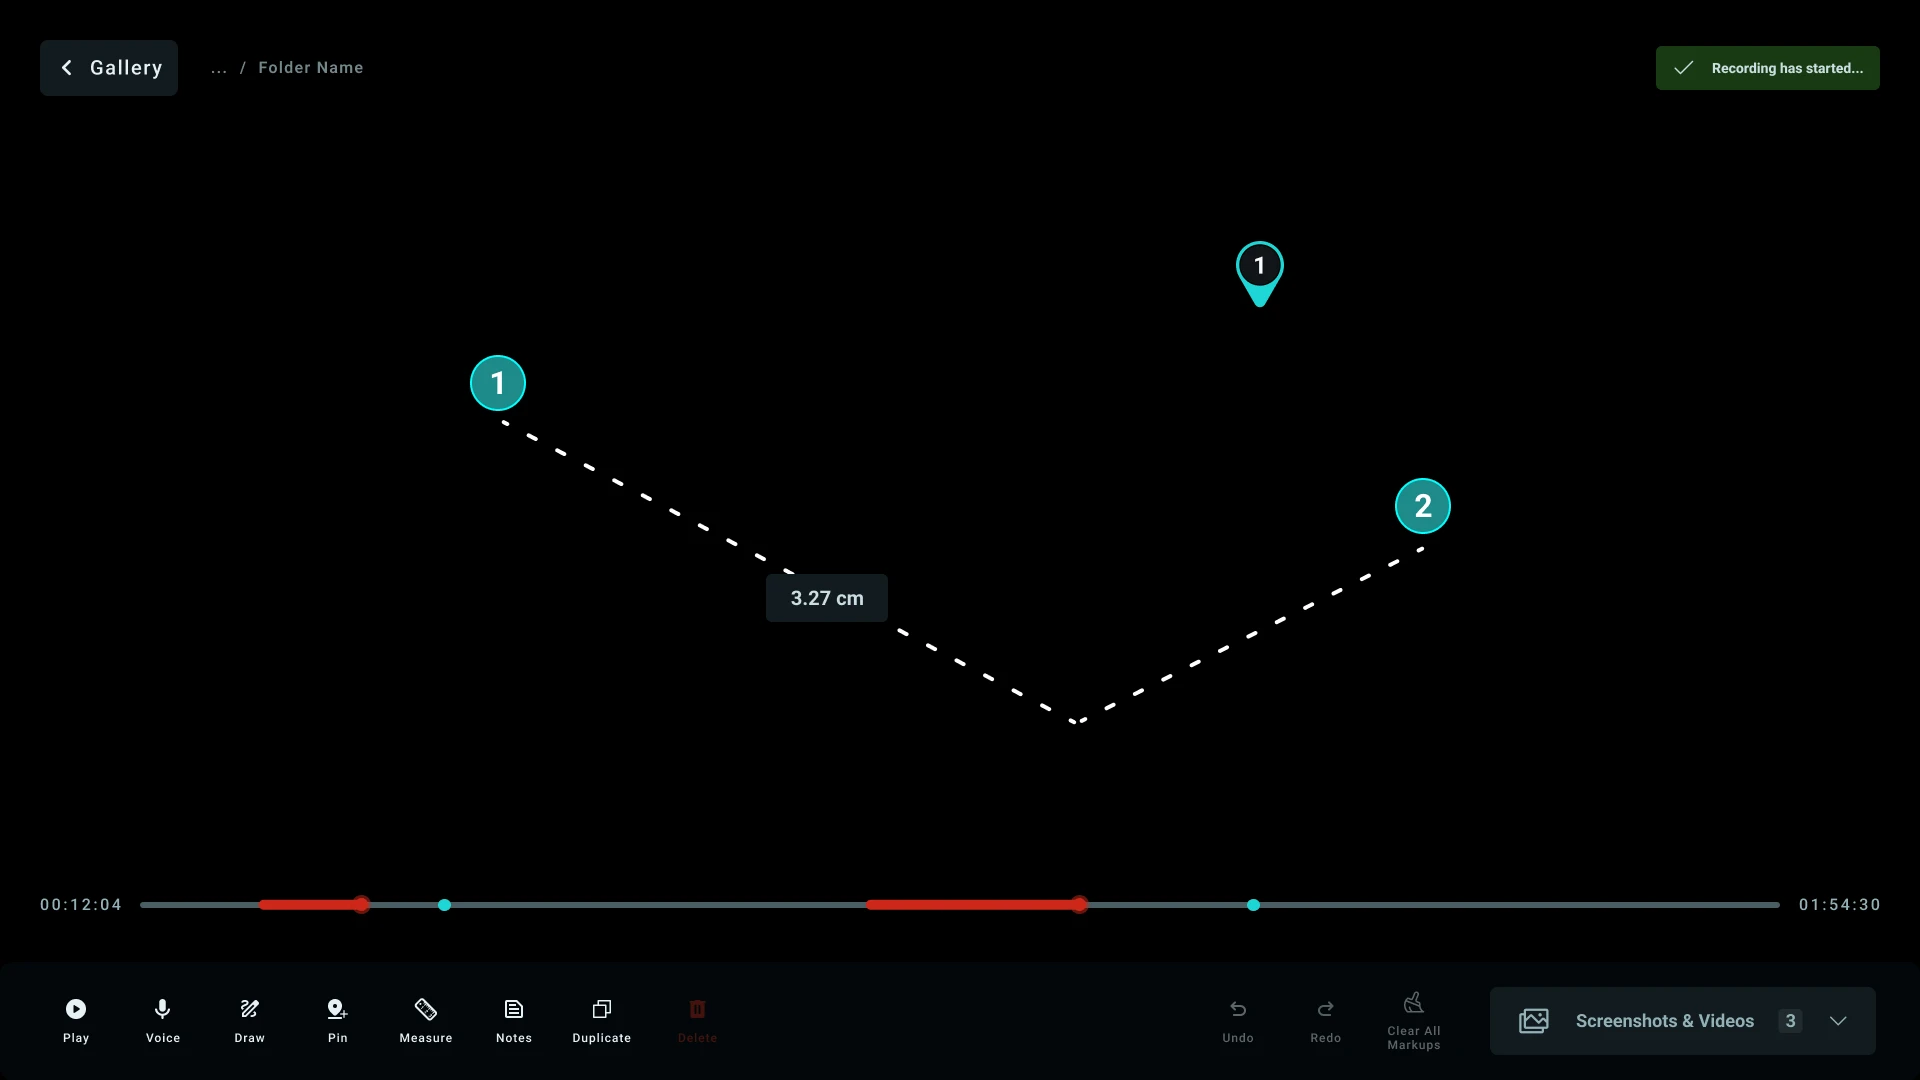
Five key decisions and what each one replaced
Annotation became a mode
A tool rail, a cyan border and a banner.
Instead of: five tool buttons always on.
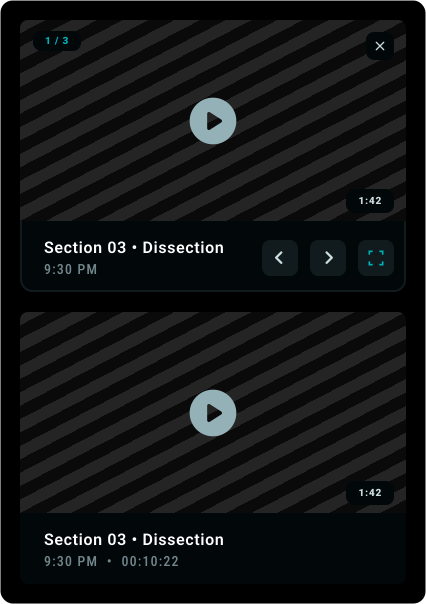
Captures in a corner player
Saved clips open in the bottom right.
Instead of: a drawer that pushed the video off center.
The wall monitor shows part of the screen
Only the video and the surgeon’s marks.
Instead of: a cluttered copy of the whole screen.
Pins got numbers
So a pin can be called out by voice.
Instead of: unnumbered pins and a side list.
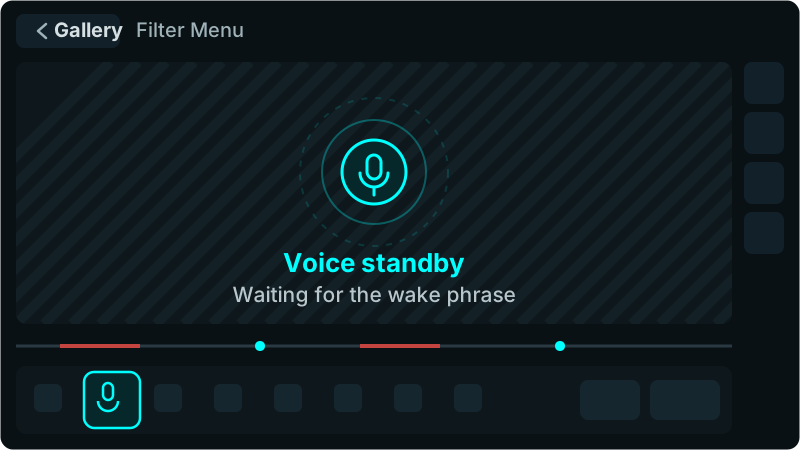
Voice commands got a visible log
Time, what was said and the reply.
Instead of: only a chime.
Project 3 · Live annotation
The tablet keeps the tools; only the video and marks go to the main screen.
Annotation is a named mode with a clear way out.
Instead of
Mirroring the whole tablet. At six feet, the toolbar was clutter.
Still to do: an Edit button. I ran out of time, so a dashed placeholder marks where it goes.
From wireframe to prototype
I built a prototype in Figma to check annotation mode, tap target size and how views switch.
I can’t show the prototype because of privacy rules. I am happy to walk through it on a call.
Resolution and impact
Outcome
- >50%less task-completion time in exploratory usability testing
- 6 of 10usability rules fixed in my own review of the prototype
Exploratory usability testing, moderated and unmoderated, with A/B tests and timed sessions, including unmoderated tests with senior software engineers, cut task-completion time by more than 50%, with fewer interaction steps and fewer observed errors.
These were exploratory tests of a prototype, so they are early signals, not product results.
Outcome
My clinical supervisor said the component system and annotation mode could be the basis for future console software.
The project ended before launch.
Heuristic evaluation
6 of 10 fixed, 4 still open.
H1 · FixedVisibility of System Status
I added 3 cues (a cyan border on the video, a top banner, and a tool rail) so surgeons knew marks were live.
H2 · Still openMatch Between the System and the Real World
I replaced engineering codes with clinical words. Some system errors still needed a review.
H3 · FixedUser Control and Freedom
I made a separate mode with a check button to exit, instead of a confusing toggle.
H4 · FixedConsistency and Standards
I used the same 4-color alert scale (green, amber, red, grey) on every console view.
H5 · FixedError Prevention
I stopped taps on a tool from leaving a mark on the live surgery video by accident.
H6 · FixedRecognition Rather than Recall
I added a word and an icon to every button, so staff did not have to remember.
H7 · Still openFlexibility and Efficiency of Use
Keyboard shortcuts worked for expert users. Custom tool presets stayed on the to-do list.
H8 · FixedAesthetic and Minimalist Design
I folded the screen into 3 regions that collapsed. This kept the video clean.
H9 · Still openHelp Users Recognize, Diagnose, and Recover from Errors
I grouped errors by robotic arm. Repeated error messages still needed to merge into one.
H10 · Still openHelp and Documentation
Help sat in the settings. I left out a full guided tour, because it could distract people in the operating room.
All three together
- Before
Arm identity
A nurse reads the arm bars and knows which arm needs help.
- During
Video editor
The surgeon marks, measures and records on the live feed.
- During
Live annotation
Marks from another screen show on the main screen.
- After
Gallery
Captures wait there, named by procedure step.
I built all three from the same components, the same severity scale and the same arm colors.
What I handed over
A working prototype
Working flows for annotation, captures, the corner player, case setup and the gallery.
A component library
One alert scale, the rules for using the existing arm colors, and the rules for how buttons act.
A test plan
A full test plan with 10 tasks and 9 ideas to test.
Still unfinished
- You could not undo one mark, only clear all.
- Repeated error alerts did not merge into one row.
- A medical expert still had to review the clinical words.
- Live annotation still needed an Edit button.
Biggest usability risk
The first two: undoing only one mark, and repeated error alerts that did not merge into one row.
What I would test next
I would have tested all versions with other stakeholders.
Takeaways
Write the reason before drawing
Name the old pattern each choice replaces.
Components before full screens
Early alert rules kept four parts consistent.
Prototype early
A running prototype caught a tap-through bug.
Design system states, not controls
Decide how modes switch before polishing buttons.
Familiar beats new when mistakes cost a lot
The corner player worked because people knew it.
Test earlier, with rougher designs
Ten minutes with a surgeon beats six versions alone.
To follow privacy and NDA rules, I changed the screens and hid all patient and staff names.